Two materials, two very different bills. Here is how composite and porcelain veneers compare on tooth preparation, appearance, durability and cost over the years, so you can judge value rather than price.
In short
|
What this guide covers
- What a veneer is, and what part of the tooth it touches
- Composite vs porcelain in plain terms
- The treatment process, step by step
- How natural each material looks
- Durability, upkeep and what can go wrong
- Cost and value over time
- Are you suitable for veneers?
- Realistic expectations and limitations
- When to see a dentist
- Frequently asked questions
What a Veneer Is, and What Part of the Tooth It Touches
A tooth has three layers that matter here. Enamel is the hard outer shell, roughly 0.5 mm to 1.5 mm thick on the front surface of an upper front tooth. Dentine sits underneath it, is softer, more yellow, and contains tiny tubules that connect to the nerve, which is why exposed dentine feels sensitive to cold. The pulp is the nerve and blood supply at the centre.
A veneer is a facing bonded over the enamel to change shape, shade, length or the look of small gaps. Two consequences follow from that simple description, and they explain most of the differences between the materials:
- The bond to enamel is more predictable and longer lasting than a bond to dentine, so a veneer that sits mostly on enamel has a better prognosis than one bonded to a heavily prepared tooth.
- Any enamel removed to make room for the veneer does not regenerate. Deeper preparation can also expose dentine, which may cause sensitivity.
This is why the preparation plan, not the brand or the material name, is the part of the quotation to read closely. At Misora, conventional porcelain veneers typically need less than 1 mm of enamel reduction, and thinner MINISH veneers, typically about 0.1 mm to 0.3 mm at the thinnest point, allow surface polishing in suitable cases.
Composite vs Porcelain in Plain Terms
Composite veneers are built from a tooth-coloured resin, a mix of a resin matrix and glass or ceramic filler particles. The dentist places it on the tooth in layers and sets each layer with a curing light. The shaping is done by hand, in the mouth, in one appointment. Little or no enamel is removed in suitable cases.
Porcelain veneers are dental ceramic, made outside the mouth. After any preparation, a digital scan or impression is taken, a laboratory fabricates the veneer, and it is bonded with resin cement at a second appointment. Because the ceramic is made and glazed under laboratory conditions, its surface and optical properties differ from resin placed chairside.
The Treatment Process, Step by Step
Assessment, before either material is chosen
- Examination and radiographs where indicated, to check for decay, cracks, old restorations and the condition of the gums.
- A bite assessment, including any signs of clenching or grinding, because those forces load the edges of a veneer.
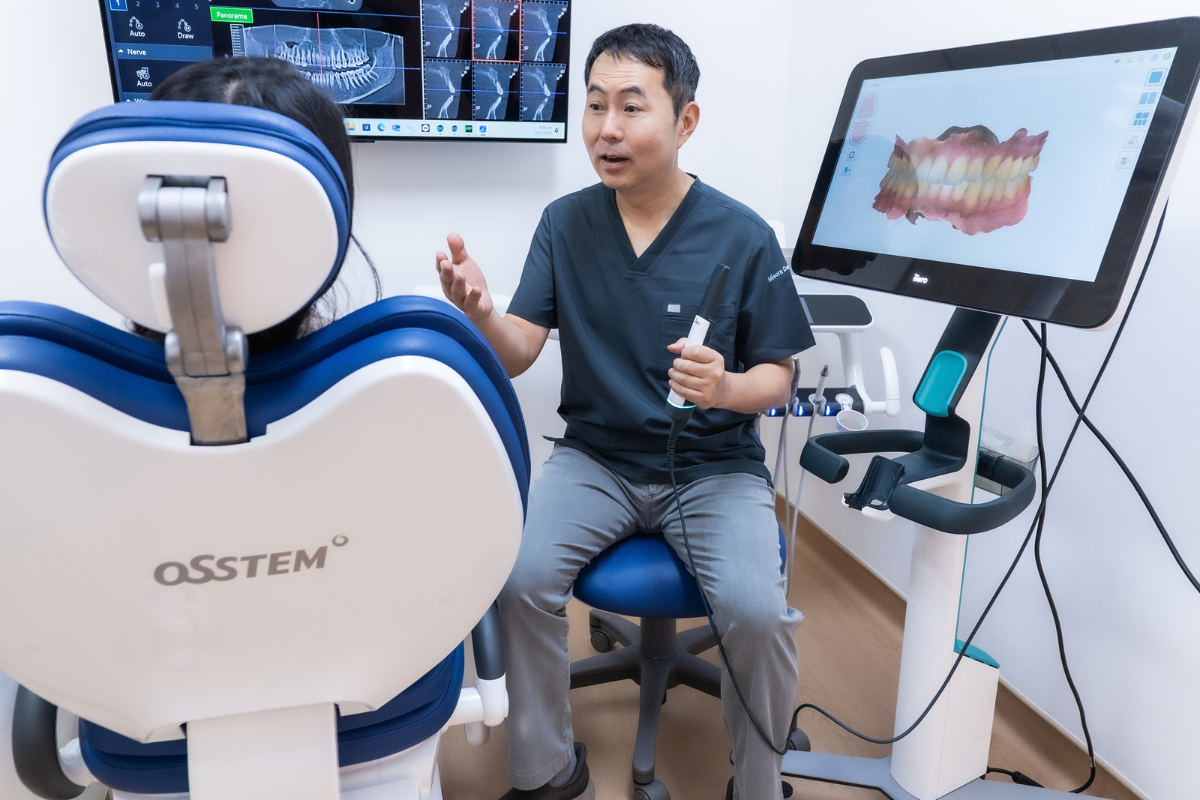
- Photographs and a digital scan, used to plan shape, length and proportion.
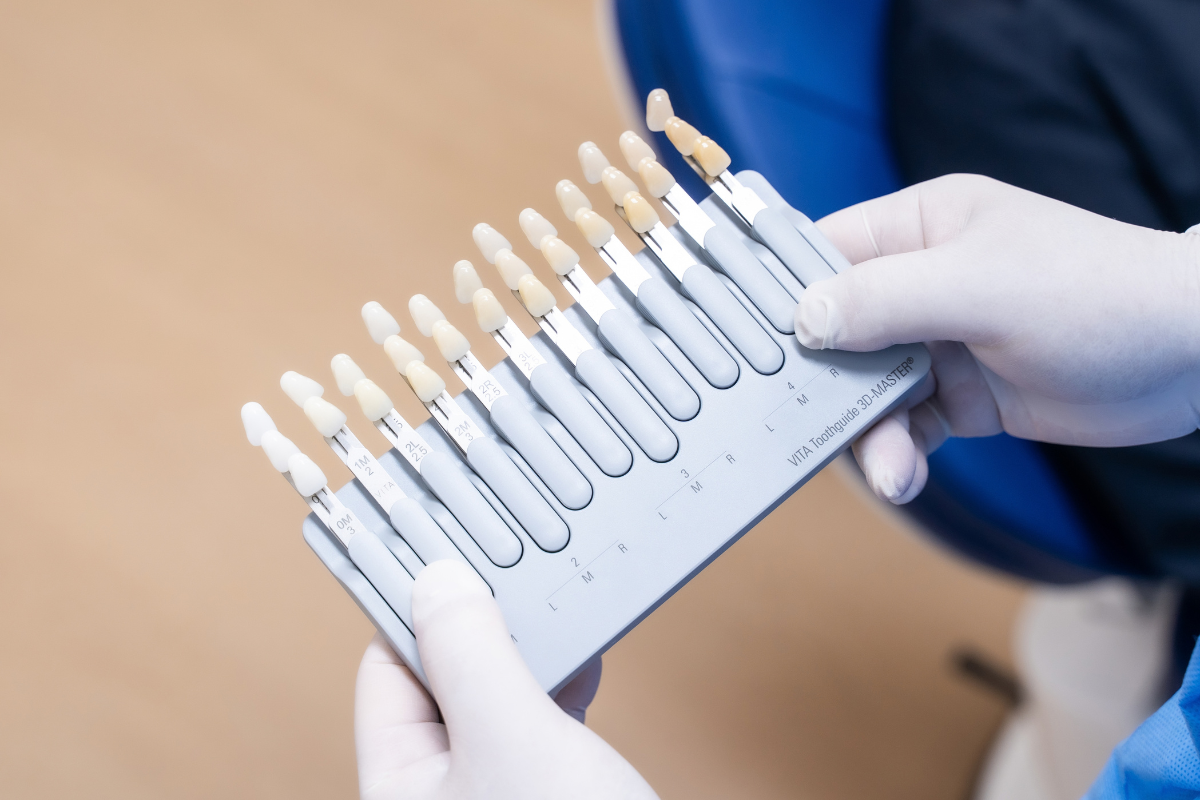
- Shade discussion. Where whitening is planned, it is normally completed first, because a veneer’s shade is fixed once made.
- A written plan and quotation setting out which teeth are involved and how much preparation each one needs.
Composite: usually one appointment
The surface is cleaned and lightly conditioned, an adhesive is applied, and resin is layered, shaped and cured. The veneer is then contoured and polished. Adjustments can usually be made on the same day, and small repairs can often be added later without remaking the whole veneer.
Porcelain: usually two appointments plus a review
At the first appointment the tooth is prepared where needed and scanned, and a temporary veneer may be placed. The laboratory then fabricates the veneer. At the second appointment it is tried in, checked for fit, contact and shade, then bonded and the bite is adjusted. A review follows to check the gum response and the margins.
How Natural Each Material Looks
Enamel is translucent and scatters light, which is why a natural tooth does not look like a flat block of colour. Dental ceramic behaves in a similar way, so porcelain tends to hold its appearance across different lighting conditions. Its glazed surface also resists staining from coffee, tea, red wine and curry.
Composite can look natural when it is layered and polished well, and a skilled hand matters more with composite than with porcelain because the shaping happens in the mouth. Over time the resin surface can pick up surface stain and can dull as it is brushed, so appearance depends partly on maintenance and on polishing at review visits. Individual experiences vary.
Durability, Upkeep and What Can Go Wrong
Composite veneers | Porcelain veneers | |
Appointments | Usually one | Usually two, plus a review |
Tooth preparation | Minimal or none in suitable cases | Minimal, decided case by case |
Typical lifespan | Around 4 to 8 years in suitable cases | Around 10 to 15 years in suitable cases |
Stain resistance | Lower; the resin surface may discolour | Higher; glazed ceramic surface |
Chipping | Can chip; often repairable chairside | Can chip or fracture; usually remade |
Upfront cost | Lower | Higher |
Medisave | Not claimable | Not claimable |
The three problems seen most often with either material are the same three:
- Decay at the margin. The joint between veneer and tooth sits near the gum line. Plaque left there causes decay in the tooth underneath, not in the veneer. Flossing that margin daily is the single most useful habit.
- Debonding. A veneer can come away, usually after a knock, a hard bite or where bonding was to dentine rather than enamel. It is often re-bondable if the veneer is intact and brought in undamaged.
- Fracture from grinding. Clenching and grinding load the incisal edge. A night guard is commonly advised where those signs are present.
Cost and Value Over Time
Composite costs less at the outset because there is no laboratory stage. Porcelain costs more and, in suitable cases, lasts longer. A composite veneer replaced twice over ten years can close much of that gap; a porcelain veneer that needs remaking early can widen it. Judge the cost across a decade, and count the appointments each route asks of you.
Two things change that arithmetic, so ask about both: whether the quotation includes reviews and polishing, and what a replacement costs if one veneer is damaged.
Veneers are cosmetic and are not Medisave-claimable. Medisave applies to selected surgical procedures under the Ministry of Health’s Table of Surgical Procedures. Fees at Misora are discussed at consultation, after assessment of your clinical condition, and you receive a written quotation listing what is and is not included.
REVIEW NOTE (internal, remove before publishing): client to confirm whether an exact veneer fee is to be published. Under the Advertisement Regulations only an exact and final price may be stated, with no “from”, no range and no comparison.
Are You Suitable for Veneers?

Suitability is a clinical judgement, not a preference. The factors checked at the assessment are:
- Enamel condition. Enough sound enamel to bond to. Heavily worn, eroded or previously restored teeth may be better served by a crown.
- Gum health. Bleeding or inflamed gums are treated before cosmetic work, because the gum margin is where the veneer finishes.
- Decay and cracks. Treated first. A veneer placed over an untreated problem hides it rather than solves it.
- Bite and grinding. Heavy clenching or an edge-to-edge bite raises the risk of chipping and may change the recommendation.
- Alignment. Where teeth are crowded or rotated, Invisalign or braces may be suggested first, because moving teeth leaves enamel untouched.
- Age and gum position. Gum levels continue to change in young patients, which can affect how a margin looks years later.
Realistic Expectations and Limitations
- Veneers change the front surface of the teeth treated.
- Neither material can be whitened once placed. Whitening lightens natural tooth only, so any whitening is planned before the shade is chosen.
- Treating one or two teeth in a front row is harder to match than treating several together, because the eye compares neighbours directly.
- Veneers are restorations with a service life, not a permanent fixture. Plan for maintenance, reviews and eventual replacement.
- Sensitivity to cold for a few days after preparation is common and usually settles. Sensitivity that persists is a reason to return.
When to See a Dentist
Book an appointment rather than waiting for your next review if you notice:
- A veneer that feels loose, catches floss differently, or comes away.
- A chip, a rough edge, or a change in how your teeth meet.
- Sensitivity to cold or sweetness that lasts beyond a couple of weeks.
- Bleeding, swelling or tenderness of the gum around a veneered tooth.
- A dark line or a shadow appearing at the gum margin.
Veneer cases at Misora are assessed and treated by Dr Kang Minsok, DDS (Columbia University, New York, USA), who has practised for over 25 years in Seoul and Singapore. His practice focuses on crowns, bridges, veneers and implant restorations. Korean and Japanese coordinators are available, so the consultation can be held in the language you prefer.