
MINISH is a porcelain veneer system fabricated by a dental laboratory in Korea. The shells are made thin enough that, in suitable cases, the tooth surface needs polishing rather than cutting. Whether your teeth are suitable is decided after a clinical examination, not before it. Korean and Japanese coordinators are available.
A veneer is a thin shell of porcelain bonded to the front surface of a tooth. MINISH is a branded veneer system made in Korea and placed at Misora by Dr. Kang. What separates it from a conventional porcelain veneer is the thickness, and what that thickness allows during preparation.
Misora places both MINISH veneers and conventional porcelain veneers. Which one suits your teeth is a clinical decision that depends on tooth position, enamel condition and bite, and it is made after assessment. If you are comparing the two, our dental veneers page covers conventional porcelain veneers in full.
Preparation is the part patients ask about most, because it is the part that cannot be undone. Enamel does not grow back. The ranges below describe the three options as they are generally reported in clinical practice, not a fixed amount for any particular tooth. What your own teeth need is determined at examination.
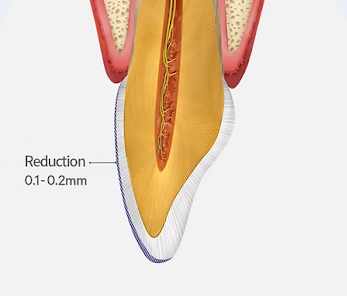
Typically less than 1 mm of enamel reduction across the front surface, with a defined margin near the gum line. Usually carried out under local anaesthetic.
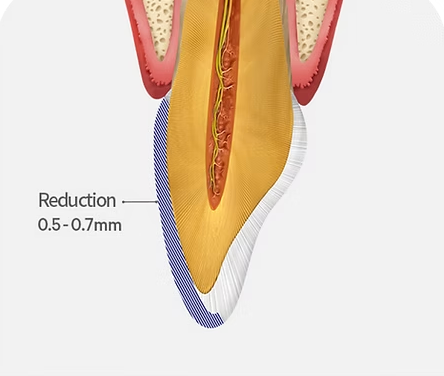
Covers the whole tooth and requires reduction on every surface. Appropriate where a tooth is heavily filled, fractured or root-treated and a veneer would have too little sound tooth to bond to.
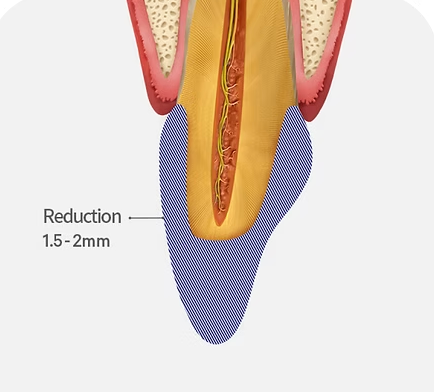
Whether a smaller preparation is the right choice depends on the tooth position, the enamel and the bite. The section below sets out what the published research says on both sides of that question.
A prospective study published in the Journal of Esthetic and Restorative Dentistry compared 55 prepless veneers with 55 minimally prepared veneers at one year. Fractures occurred in 9.1 per cent of the prepless group and in none of the minimally prepared group, a statistically significant difference. The authors concluded that a small amount of preparation may improve stability, and that case selection and bite management matter more than preparation technique on its own. This is why Misora does not present no-preparation treatment as a default, and why we will tell you when your teeth are better served by a conventional veneer.
1. Alqutaibi AY, Saker S, Alghauli MA, Algabri RS, AbdElaziz MH. Clinical survival and complication rate of ceramic veneers bonded to different substrates: a systematic review and meta-analysis. J Prosthet Dent. 2025;134(4):1030-1039. doi:10.1016/j.prosdent.2024.03.019
2. Smielak B, Armata O, Bojar W. A prospective comparative analysis of the survival rates of conventional vs no-prep/minimally invasive veneers over a mean period of 9 years. Clin Oral Investig. 2022;26(3):3049-3059. doi:10.1007/s00784-021-04289-6
3. Yilmaz S, Demirkol N, Eyuboglu TF, Ozcan M. Clinical performance comparison of prepless and minimally invasive ceramic laminate veneer restorations: a prospective clinical study. J Esthet Restor Dent. 2026;38(4):725-732. doi:10.1111/jerd.70077
These studies examine no-preparation and minimally prepared ceramic veneers as a category. They are not studies of the MINISH system specifically. We cite them because they are the evidence that exists, and we would rather show you that than make a claim we cannot support.
| Generally suitable | Addressed first, or not suitable |
|---|---|
|
|
Three stages, with a decision point before anything irreversible happens. Nothing is started on the day of the first visit.
The purpose of the first visit is to establish whether MINISH veneers suit your teeth at all, and to say so plainly if they do not.
The veneers are designed from your scan and made to that specification.
Fitting is done under isolation, with the bite checked before the veneers are bonded rather than after.
MINISH veneers are not Medisave-claimable. Fees are discussed at consultation and quoted as exact amounts.
Patients ask about travelling to Seoul for this treatment, and it is a fair question to ask. The clinical procedure is the same procedure wherever it is carried out. The practical differences are about what happens afterwards.
Bonded porcelain needs review. Margins, contact points and gum response are checked at about two weeks and again at routine appointments.
Adjustments are ordinary rather than a sign something has gone wrong. They are simpler to arrange with the clinician who placed the veneers.
If a veneer chips or debonds, the clinician who holds your scan, shade record and laboratory specification is best placed to replace it.
Your records stay in one file: the scan, the shade, the laboratory specification and your clinical notes.
Consultations at Misora can be conducted in Korean or Japanese where you prefer.
This is information for your own decision, not a recommendation against treatment elsewhere. If you have already had veneers placed overseas and would like them reviewed, we are happy to assess them.
Fees depend on the number of teeth treated and the clinical complexity of the case. After examination you are given an exact figure in writing, before anything is agreed. We will not quote a fee before we have examined your teeth.
MINISH veneers are an aesthetic restoration and are not Medisave-claimable. Where a tooth separately requires treatment that may be claimable, that is set out on its own and explained before it begins.

Sometimes, and it depends on where your teeth sit. Where a tooth already sits behind the line of the intended veneer, surface polishing may be all that is needed. Where a tooth sits forward of that line, some enamel reduction is required so the finished veneer does not stand proud of the arch. Dr. Kang will tell you which applies to each tooth after examining you. We do not describe the treatment as no-preparation before we have looked at your teeth.
There is no single figure, because the thickness is decided tooth by tooth. Where a tooth already sits behind the line of the intended veneer, the shell can be made at its thinnest, from about 0.1 mm. Where a tooth sits forward of that line, or where more contour or shade correction is needed, the veneer is made thicker. In most cases the finished shell falls between about 0.1 mm and 0.3 mm, measured at the thinnest point of the front surface. Thickness is matched to the tooth rather than minimised for its own sake. We will give you the expected thickness for your own teeth after the scan, and the laboratory works to that specification.
Not in the ordinary sense of the word. Even where no enamel is removed, the veneer is bonded with an adhesive layer, and removing it means cutting that layer away, which affects the tooth surface. Treatment should be planned on the basis that it is a long-term decision. This is one reason the mock-up stage exists.
There is no lifespan that can be promised, because longevity depends on bite forces, grinding habits, gum health and maintenance. Published research on ceramic veneers bonded to enamel reports high survival at follow-up periods of nine years and beyond, and bonding to enamel rather than exposed dentine is associated with fewer failures. Your own result depends on your own clinical circumstances.
Where the tooth surface is only polished, local anaesthetic is often not required. Where enamel reduction is needed, local anaesthetic is used for comfort. Mild sensitivity for a few days afterwards is common. What to expect is explained at each stage before it happens.
Fees depend on the number of teeth treated and the complexity of the case. A written estimate, quoted as an exact amount, is provided at consultation after a clinical examination. Misora does not advertise veneer prices.
No. Veneers are classified as an aesthetic procedure and are not Medisave-claimable under CPF Board rules.
Porcelain does not respond to whitening agents. If you want a lighter base shade, whitening is carried out before the veneers are made so that the laboratory can match to the final shade. Whitening afterwards would change the natural teeth and not the veneers, which can leave a mismatch.
Same principle, different preparation. Our dental veneers page covers conventional porcelain veneers, which typically require under 1 mm of enamel reduction. MINISH veneers are thinner, which in suitable cases allows surface polishing instead. Both are assessed at the same consultation and you are not asked to choose between them in advance.
Start with an examination and a clear answer on whether your teeth suit this treatment. Fees are shared transparently at consultation.